Short answer
Pharmaceutical method validation is the documented proof that an analytical procedure is fit for its intended purpose: identity, impurity, assay or another quantitative test on a drug substance or product. Since 1 November 2023 the governing text is ICH Q2(R2), adopted together with ICH Q14 on analytical procedure development.[1][2]
What gets validated depends on the test. An assay needs specificity, response over the reportable range, accuracy, repeatability and intermediate precision. An impurity limit test needs specificity and a detection limit. An identity test needs specificity only. ICH Q2(R2) tells you what to show and the minimum data. It does not fix numeric pass limits like 2% RSD or r ≥ 0.999. Those are site policy and must be written into your validation protocol before the study starts.
What pharmaceutical method validation has to prove
A validated analytical procedure gives a reportable result you can defend. ICH Q2(R2) puts it in lifecycle terms: a validation study is designed to “provide sufficient evidence that the analytical procedure meets its objectives”. Those objectives are expressed as performance characteristics, each with a criterion you set in advance.[1] In practice that means proving four things about the procedure you will actually run in QC:
- It measures the right thing. This is specificity or selectivity. Excipients, impurities, degradation products and the matrix must not bias the result. Where one procedure cannot be fully specific, Q2(R2) allows a second, supporting procedure to compensate.
- It responds properly across the range you will report. This is response and range. For impurities it includes the lower range limit, expressed as the quantitation limit (QL) or detection limit (DL).
- It gets close to the true value. This is accuracy.
- It gives the same answer when repeated. Q2(R2) calls this precision. It splits into repeatability, intermediate precision across days, analysts and equipment, and reproducibility between laboratories.
Q2(R2) applies to release and stability testing of commercial drug substances and products. It can also be applied, risk-based, to other procedures in the control strategy, and in a phase-appropriate manner during clinical development.[1] The revision brings in two things Q2(R1) did not have: guidance for multivariate procedures (NIR models, for example), and language that treats validation as one stage of a lifecycle rather than a one-time event. Both run through the rest of this page.
Which rules apply to method validation in pharma in 2026
Four instruments govern pharmaceutical method validation for a lab supplying India, the US or Europe. None of them sets a numeric acceptance criterion for precision or linearity.
| Instrument | What it requires | Status |
|---|---|---|
| ICH Q2(R2) Validation of Analytical Procedures | Performance characteristics by test type, recommended data, reportable ranges | Final, adopted 1 Nov 2023[1]. FDA final guidance March 2024[3]. EMA effective 14 Jun 2024, replacing Q2(R1) (CPMP/ICH/381/95)[4] |
| ICH Q14 Analytical Procedure Development | Development, robustness, system suitability, lifecycle change management | Final, adopted 1 Nov 2023[2] |
| 21 CFR 211.165(e) and 211.194(a)(2) | Accuracy, sensitivity, specificity and reproducibility of test methods “shall be established and documented”. Compendial methods need no revalidation, but their suitability “shall be verified under actual conditions of use” | In force (US)[5][6] |
| Revised Schedule M, G.S.R. 922(E), 28 Dec 2023 | Part I 5.11: “particular attention” to validation of analytical test methods. Part XII (APIs) 12.8.1 to 12.8.4: validate unless compendial, verify compendial methods, cover the characteristics “within the ICH guidelines”, qualify equipment first, record every modification | In force (India)[7] |
Swipe the table sideways on a phone.
A detail worth knowing before an inspection: the notified Schedule M text refers to “the ICH guidelines on validation of analytical methods” but never names Q2 by number. We searched the full 124-page gazette text for “Q2” and found no occurrence.[7] Indian inspectors will therefore read “ICH” as the current revision. A protocol template that still cites Q2(R1) is out of date on its face.
FDA’s separate 2015 guidance, Analytical Procedures and Methods Validation for Drugs and Biologics, is still listed on FDA’s site as a final guidance.[8] For compendial procedures, USP general chapter <1225> (validation) and <1226> (verification) remain the reference texts. They are covered in the next section.
Validation tests by procedure type: ICH Q2(R2) Table 1
This is the table most QC labs build their protocols from. It is reproduced here in the same structure as the guideline. “+” means the test is normally conducted; “−” means it is not.[1]
| Characteristic | Identity | Impurity: quantitative | Impurity: limit test | Assay (content, potency, other quantitative) |
|---|---|---|---|---|
| Specificity / selectivity | + | + | + | + |
| Response (calibration model) | − | + | − | + |
| Lower range limit | − | QL (DL in complex cases) | DL | − |
| Accuracy | − | + | − | + |
| Repeatability | − | + | − | + |
| Intermediate precision | − | + | − | + |
Footnotes in the guideline: accuracy and precision may be evaluated together in a combined approach. Intermediate precision need not be studied separately where reproducibility data already cover it. “Other quantitative measurements” follow the impurity scheme when the range limit is close to the DL/QL, and the assay scheme when it is not.
Two differences from the Q2(R1) table many SOPs still copy. Linearity is now “response”, because Q2(R2) explicitly accommodates non-linear calibration models such as immunoassay curves. DL and QL are now the “lower range limit” rather than stand-alone characteristics.[1]
The USP category view of the same decision
Labs that follow USP classify procedures into four categories under general chapter <1225>. The historical USP text available to us lists the data elements below. Category I covers assay of major components, Category II impurities, Category III performance tests such as dissolution, and Category IV identification.[9]
| Characteristic | Cat. I | Cat. II quant. | Cat. II limit | Cat. III | Cat. IV |
|---|---|---|---|---|---|
| Accuracy | Yes | Yes | * | * | No |
| Precision | Yes | Yes | No | Yes | No |
| Specificity | Yes | Yes | Yes | * | Yes |
| Detection limit | No | No | Yes | * | No |
| Quantitation limit | No | Yes | No | * | No |
| Linearity | Yes | Yes | No | * | No |
| Range | Yes | Yes | * | * | No |
check source The current official USP–NF text is subscription-only, and a proposed revision published in Pharmacopeial Forum 51(6) would retitle the chapter “Validation of Analytical Procedures” and align it with ICH Q2(R2) and USP <1220>. The comment period closed 31 January 2026.[10] Confirm the official version in your USP–NF subscription before citing categories in a protocol.
Reportable ranges and minimum data
Q2(R2) Table 2 gives example reportable ranges. Other ranges are acceptable if justified.[1]
| Use of the procedure | Low end | High end |
|---|---|---|
| Assay of a product | 80% of declared content or of the lower specification limit | 120% of declared content or of the upper specification limit |
| Potency | Lowest specification limit − 20% | Highest specification limit + 20% |
| Content uniformity | 70% of declared content | 130% of declared content |
| Dissolution, immediate release (one-point specification) | Q − 45% of the lowest strength | 130% of declared content of the highest strength |
| Dissolution, multi-point specification or modified release | Lower limit of the reportable range as justified, or QL | 130% of declared content of the highest strength |
| Impurity | Reporting threshold | 120% of the specification limit |
| Purity (as area %) | 80% of the lower specification limit | Upper specification limit or 100% |
Where assay and impurities are run as a single test against one standard, response must be shown from the impurity reporting level up to 120% of the assay specification limit.
Minimum number of determinations
| Characteristic | Minimum design stated in Q2(R2) | What to report |
|---|---|---|
| Response (linear) | At least 5 concentrations spread across the range | Plot, correlation coefficient or r², slope, y-intercept, and an assessment of the residuals |
| Accuracy | For example 3 concentrations × 3 replicates of the full procedure, covering the reportable range | Mean % recovery (or difference from the true value) with a 100(1−α)% confidence interval |
| Repeatability | 9 determinations across the range (e.g. 3 × 3), or 6 determinations at 100% of test concentration | SD, RSD and a confidence interval |
| Intermediate precision | Days, environmental conditions, analysts, equipment “as relevant”. Factors need not be studied one at a time, and DoE is encouraged | SD, RSD and a confidence interval |
| DL / QL by signal-to-noise | S/N 3:1 for DL; at least 10:1 for QL | Chromatogram or trace at the limit |
| DL / QL by SD and slope | DL = 3.3σ/S; QL = 10σ/S. σ from the blank, the residual SD of a regression line, or the SD of y-intercepts | σ, S, the method used, and confirmation at the limit |
All of this is in sections 3.2 and 3.3 of the guideline.[1] One change deserves emphasis. For accuracy and precision, Q2(R2) now asks for a confidence interval and states that “the observed interval should be compatible with the corresponding … acceptance criteria”. A mean recovery of 99.6% no longer settles the question on its own if the interval around it runs outside your limit.
Where validation sits in the method lifecycle
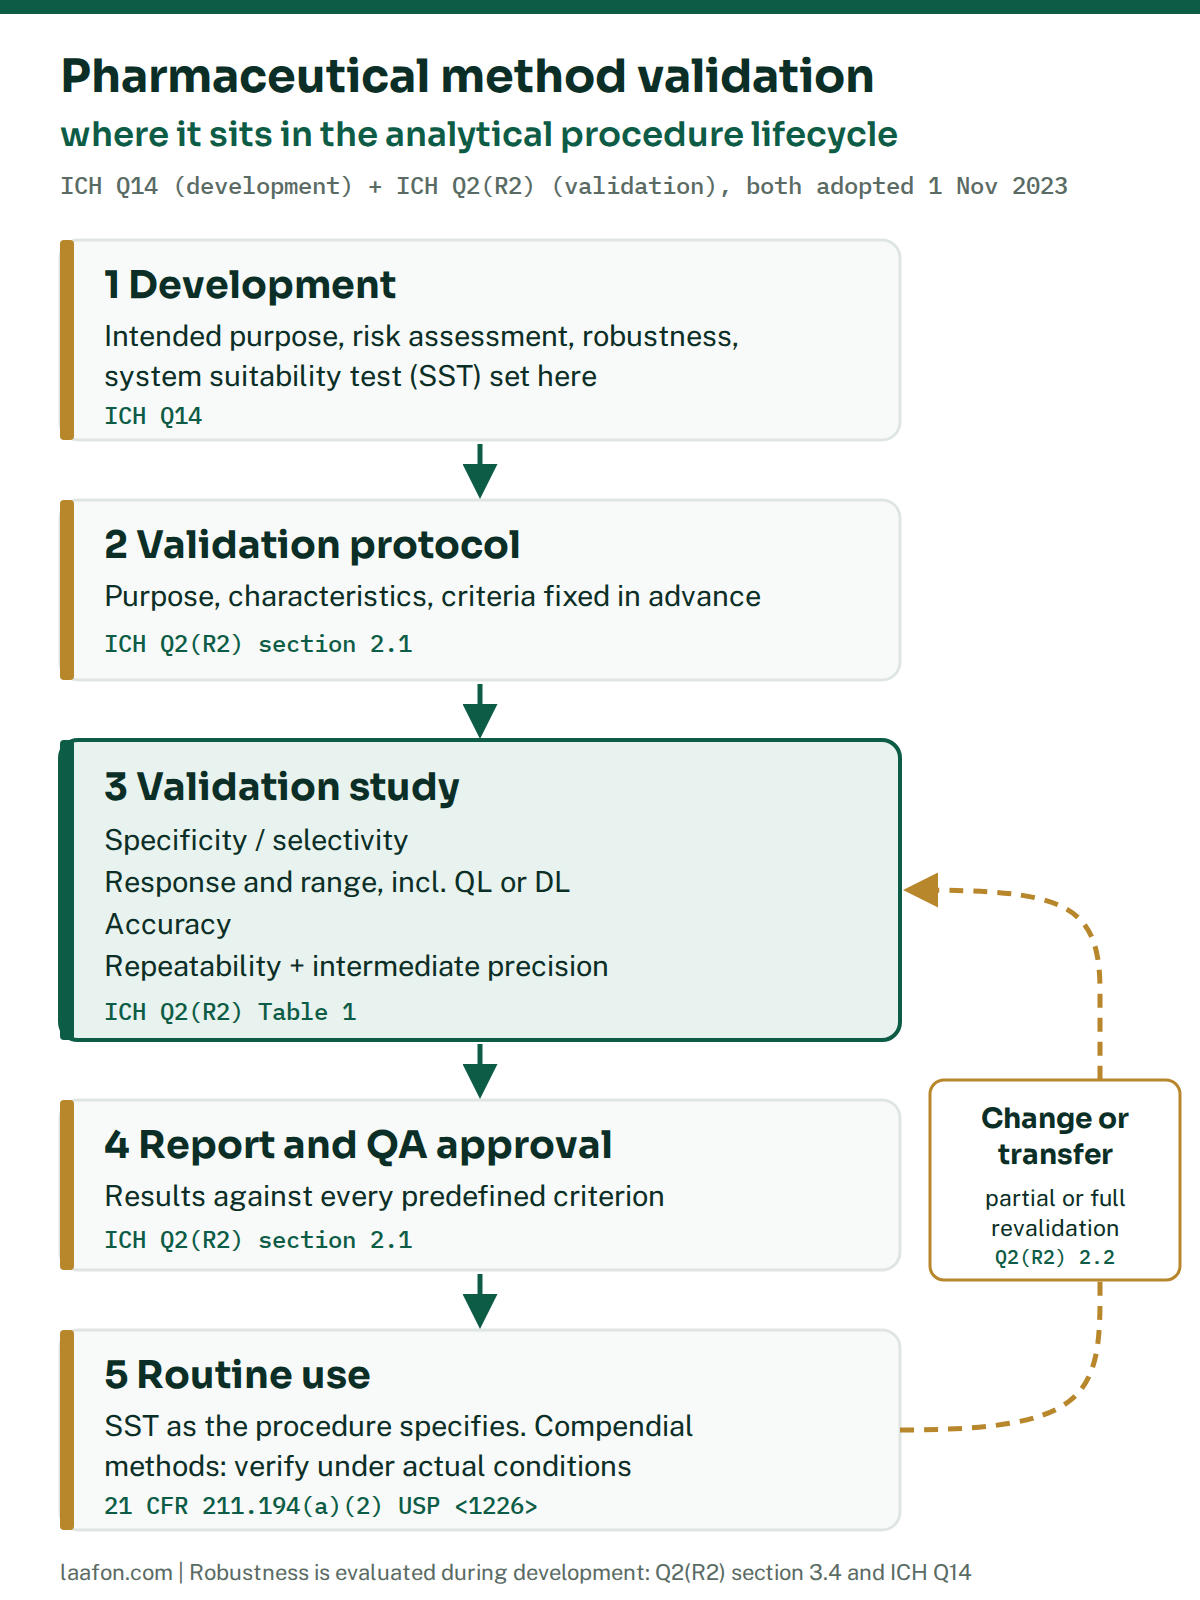
ICH Q14 and Q2(R2) were written as a pair. Development work generates the knowledge used to design the validation study. That includes the robustness data and the system suitability test, which Q2(R2) calls “an integral part of analytical procedures”, generally established during development.[1][2] After approval, changes are handled through the lifecycle. Q2(R2) section 2.2 says “partial or full revalidation may be required”, and that science and risk-based principles can justify which characteristics need re-testing.[1] On the API side, Schedule M Part XII adds a record-keeping duty. Every modification of a validated method needs its reason and data showing the modified method is “as accurate and reliable as the established method”.[7]
6 common method validation mistakes in pharma, and what the texts actually say
Each of these appears in published pharmaceutical method validation SOP templates and blog posts, including the earlier version of this page. Each was checked against the primary document.
1. Treating in-house acceptance criteria as ICH limits
The Q2(R2) text contains no “2%”, no “0.99”, no “98” and no “102”. We searched the final guideline for each string. For linearity it asks for the correlation coefficient or coefficient of determination, the slope, the intercept and a residual analysis, and sets no threshold.[1] These figures are widely used industry conventions. They are legitimate as site policy, but they must be justified against the product specification and written into the protocol. When an auditor asks “where does 2% come from?”, the answer “ICH” is wrong.
2. Running robustness as a late validation test
Robustness is not a row in Q2(R2) Table 1. Section 3.4 says it “should be considered during the development phase”. The data can be submitted as part of development data case by case, or made available on request, with ICH Q14 as the detailed reference.[1][2] Robustness work done for the first time after validation is too late. It is the evidence that should have set your system suitability limits.
3. Re-validating compendial methods instead of verifying them
US and Indian rules both draw the same line. A method taken unmodified from the current pharmacopoeia or another recognised standard reference is not revalidated. Its suitability is verified under actual conditions of use.[6][7] USP <1226> says full revalidation is not required for verification. Specificity is the key parameter for assays, and DL/QL and precision are useful for impurity methods. It names basic procedures such as loss on drying, residue on ignition and pH as not requiring verification.[11] Modify the method, though, and it is no longer compendial. It then needs validation of the changed characteristics.
4. Treating method transfer as automatic full revalidation
Q2(R2) section 2.2 gives options. When a validated procedure goes to another laboratory, “a partial or full revalidation … and/or comparative analysis of representative samples should be performed”, with a justification if no transfer experiments are done. Co-validation across sites can satisfy transfer at the participating sites.[1] Scope the transfer protocol by risk, meaning which characteristics the new equipment, analysts and environment could affect. Do not default to repeating the whole study.
5. Using the ordinary impurity threshold for mutagenic impurities
0.05% is the ICH Q3A(R2) reporting threshold for ordinary impurities in a drug substance dosed at up to 2 g/day.[12] Mutagenic (genotoxic) impurities are controlled under ICH M7, where the threshold of toxicological concern is 1.5 µg/day.[13] At a 1 g/day dose, 1.5 µg/day works out to 1.5 ppm, or 0.00015%. That is more than 300 times lower than 0.05%. A QL at 0.05% would miss the limit entirely. The QL has to be derived from the M7 acceptable intake and the maximum daily dose of the specific product, which often calls for a more sensitive technique than the related-substances method.
6. Citing a superseded guideline in the protocol
EMA’s Q2(R2) page lists CPMP/ICH/381/95 as the Q2(R1) text it replaces, effective 14 June 2024, and FDA issued Q2(R2) as final guidance in March 2024.[4][3] A protocol written in 2026 should cite Q2(R2) and Q14. Some links still point at the 2022 Step 2 consultation draft of Q2(R2), which is not the adopted text. Whether methods already validated under Q2(R1) need a gap assessment is a decision for your change-control and periodic review process.
Validation, verification or transfer? Decide for your method
Pick where the procedure comes from and what it measures. The verdict names the activity and the characteristics to test, following ICH Q2(R2) Table 1, section 2.2 and the compendial verification rule.
1. Where does the procedure come from?
2. What does it measure?
Choose one option from each group
The verdict and the characteristics to test will appear here.
A decision aid, not a regulatory determination. Your change-control and validation master plan govern the final scope.
Linearity, DL and QL calculator (ICH Q2(R2) 3.2.3.3)
Paste your concentrations and responses. The calculator fits a least-squares line and reports the slope, intercept, r and r². It then applies the Q2(R2) formulas DL = 3.3σ/S and QL = 10σ/S, using the residual standard deviation of the regression line as σ. That is one of the σ estimates the guideline allows.[1] For a DL/QL estimate, the guideline expects the calibration samples to lie in the DL/QL region, not across the assay range. The pre-filled numbers are illustrative only.
Confirm an estimated DL or QL by analysing samples at that level before adopting it. The calculated number alone is not the validated limit. Any pass criterion you apply to r or r² is site policy, not an ICH figure.
SOP: Analytical method validation in a pharmaceutical QC laboratory
An adaptable pharmaceutical method validation SOP for chromatographic and spectrophotometric procedures. Fill the blanks from your own QMS. Nothing in the header is meant to be copied as-is.
1.0 Purpose
To define how analytical procedures used for release and stability testing are validated, verified, transferred and revalidated, so that every reportable result comes from a procedure shown to be fit for its intended purpose.
2.0 Scope
Applies to non-compendial and modified compendial procedures for drug substances, excipients where applicable, intermediates and finished products tested in the QC laboratory: identity, assay, content uniformity, dissolution, related substances and residual solvents. It also covers verification of unmodified compendial procedures and receipt of transferred procedures.
Excludes: microbiological method validation, cleaning-validation swab/rinse recovery studies, computerised-system validation and equipment qualification. Each has its own SOP. Equipment must already be qualified before this SOP applies.
3.0 Responsibility
- Analyst: executes the protocol, records raw data contemporaneously, reports deviations immediately.
- Officer / Executive QC: drafts the protocol and report, reviews data and calculations, checks audit trails.
- Head QC: approves protocol and report technically; ensures instruments and reference standards are qualified.
- Head QA: approves protocol, deviations and final report; owns change control and periodic review.
4.0 Materials and equipment
- Qualified instrument(s) with current calibration status. Schedule M Part XII 12.8.3 requires equipment qualification to be considered before validation starts.
- Reference standard or qualified working standard with certificate and assigned potency.
- Placebo or blank matrix, known impurities, and stressed (forced-degradation) samples for specificity.
- Reagents and solvents of the grade stated in the procedure; volumetric glassware class A.
- Validated calculation template or LIMS / CDS with audit trail enabled.
5.0 Procedure
6.0 Acceptance criteria
Criteria marked ICH Q2(R2) are requirements or recommendations in the guideline. Criteria marked site policy are common industry conventions that you must justify against the product specification.
| Characteristic | Criterion | Basis |
|---|---|---|
| Specificity | No interference at the analyte retention time from blank/placebo; critical pair resolved; analyte peak pure in stressed samples | ICH Q2(R2) 3.1; numeric resolution limit from SST |
| Response | ≥ 5 levels; residuals random; r or r², slope, intercept reported | ICH Q2(R2) 3.2.1 |
| Response, numeric | e.g. r ≥ 0.999 (assay) / ≥ 0.99 (impurities); intercept ≤ ___% of 100% response | site policy not stated in ICH Q2(R2) |
| Range | Accuracy, precision and response acceptable across the Table 2 range | ICH Q2(R2) 2.3, Table 2 |
| DL / QL | S/N ≥ 3:1 (DL), ≥ 10:1 (QL); QL ≤ reporting threshold of the product | S/N: ICH Q2(R2) 3.2.3. QL versus threshold: check source ICH Q3A(R2) / Q3B(R2) analytical-procedure sections |
| Accuracy | Confidence interval of mean recovery within the protocol limit (e.g. 98.0–102.0% for DS assay) | Interval: ICH Q2(R2) 3.3.1.4. Numeric limit: site policy |
| Repeatability | RSD within protocol limit (e.g. ≤ 2.0% assay; wider for impurities near QL) | Metric: ICH Q2(R2) 3.3.2.4. Numeric limit: site policy |
| Intermediate precision | Overall RSD and difference between sets within protocol limit | site policy |
| Solution stability | Response change within protocol limit over the hold time used in routine testing | site policy linked to Q2(R2) 3.4 |
Swipe the table sideways on a phone. For compendial verification, use the monograph’s system suitability and your USP <1226> or pharmacopoeial general-notice requirements. check source The Indian Pharmacopoeia general notices on verification were not retrievable for this review and are not quoted.
7.0 Frequency and revalidation triggers
ICH Q2(R2) ties revalidation to change, scoped by risk (section 2.2), rather than to a calendar interval.[1] Typical triggers written into site change-control SOPs are listed below site policy:
- Change in the drug substance route of synthesis or supplier, or in the product composition.
- Change to the procedure beyond the allowable adjustments of the applicable pharmacopoeia (for example column dimensions or gradient outside those allowances).
- Transfer to another laboratory (section 2.2 transfer options).
- Adverse trends in system suitability, OOS rate or periodic review that point at the method.
8.0 Precautions
- Never set or change acceptance criteria after seeing the data. Auditors compare protocol and report approval dates.
- Keep audit trails on for every CDS injection, including trial and “system check” injections.
- Use the same sample preparation, replicate scheme and reportable-result calculation as routine testing (Q2(R2) 2.1).
- Handle mutagenic-impurity and potent-compound standards under the relevant safety SOP.
9.0 Deviation handling
A result outside a protocol criterion is a validation deviation, not an OOS on a batch. Stop the affected experiment, record the deviation, and investigate for assignable cause (preparation error, instrument fault, standard). Repeat only under the approved investigation. If the method itself is the cause, return to development (ICH Q14), amend the procedure and re-execute the affected characteristics under a protocol amendment. QA decides whether the whole study must be repeated.
10.0 Annexures
Annexure-I: Validation summary report (below) · Annexure-II: Characteristic selection checklist (ICH Q2(R2) Table 1) · Annexure-III: Deviation log · Annexure-IV: Transfer comparison sheet.
Annexure-I: Validation summary report
| Characteristic | Design (levels × replicates) | Acceptance criterion | Result | Complies (Y/N) | Raw data ref. |
|---|---|---|---|---|---|
| Specificity | |||||
| Response / linearity | |||||
| Range | |||||
| QL / DL | |||||
| Accuracy | |||||
| Repeatability | |||||
| Intermediate precision | |||||
| Solution stability |
11.0 Revision history
| Version | Effective | Change | Change control no. |
|---|---|---|---|
| 00 | DD-MMM-YYYY | New SOP (ICH Q2(R1) based) | CC/___ |
| 01 | DD-MMM-YYYY | Aligned to ICH Q2(R2) and Q14; response and lower range limit terminology; confidence intervals added; robustness moved to development | CC/___ |
12.0 References
ICH Q2(R2); ICH Q14; 21 CFR 211.165(e) and 211.194(a)(2); revised Schedule M (G.S.R. 922(E)) Part I 5.11 and Part XII 12.8; USP <1225> and <1226>. Full citations are in the References section below.
If your validation package will be reviewed in an inspection, read it alongside the method it supports. The HPLC system suitability limits page covers the SST numbers your specificity and precision data should agree with. The UV-Visible spectrophotometer qualification SOP covers the instrument qualification that must come first. The USFDA pre-approval inspection checklist shows where method validation sits in a PAI.
Validation package going into an audit or a dossier?
Laafon Galaxy reviews analytical method validation protocols and reports against ICH Q2(R2), Q14 and revised Schedule M. We check for criteria set after the data, missing confidence intervals and superseded references before an inspector finds them. See the regulatory compliance consultation.
Method validation in pharma: FAQs
No. Q2(R2) was adopted by ICH on 1 November 2023. EMA made it effective on 14 June 2024, replacing CPMP/ICH/381/95 (Q2(R1)), and FDA issued it as final guidance in March 2024. New protocols should cite Q2(R2) and Q14. Whether methods already validated under Q2(R1) need a gap assessment is decided through your change-control and periodic review process.
No. The guideline asks you to report the standard deviation, relative standard deviation and a confidence interval for precision, and the correlation coefficient or r², slope and intercept for linearity. It does not state numeric pass limits for any of them. Limits such as 2% RSD or r of 0.999 are site policy and must be justified and fixed in the protocol before the study.
Not if they are used unmodified. 21 CFR 211.194(a)(2) and revised Schedule M Part XII 12.8.1 both require a compendial method’s suitability to be verified under actual conditions of use rather than revalidated. USP general chapter 1226 describes that verification, with specificity as the key parameter for assays. Any modification turns the method into a non-compendial one that needs validation.
ICH Q2(R2) recommends at least five concentrations for a linear response. For accuracy it gives the example of three concentrations with three replicates each across the reportable range. For repeatability it asks for nine determinations across the range or six at 100% of the test concentration. The replicate scheme should also mirror how routine results are generated.
It is still required knowledge, but it belongs to development. ICH Q2(R2) section 3.4 says robustness should be considered during the development phase and can be submitted with development data or made available on request, referring to ICH Q14. It is not one of the tests in Q2(R2) Table 1. Robustness results are what justify your system suitability limits.
ICH Q2(R2) is written for release and stability testing of commercial products, and says its scientific principles can be applied in a phase-appropriate manner during clinical development. Define the phase-appropriate scope in your validation plan, document the rationale, and agree it with the regulator where your submission requires it.
Validation proves a new or modified procedure is fit for purpose across the Table 1 characteristics. Verification shows an unmodified compendial procedure works on your product, equipment and analysts. Transfer shows a validated procedure performs equally in a receiving laboratory, through comparative testing, partial or full revalidation, or co-validation as described in ICH Q2(R2) section 2.2.
Related on laafon.com
References
- International Council for Harmonisation. ICH harmonised guideline Q2(R2): Validation of analytical procedures. Final version adopted 1 November 2023. Geneva: ICH; 2023. Available from: database.ich.org/sites/default/files/ICH_Q2%28R2%29_Guideline_2023_1130.pdf. Accessed September 2026.
- International Council for Harmonisation. ICH harmonised guideline Q14: Analytical procedure development. Final version adopted 1 November 2023. Geneva: ICH; 2023. Available from: database.ich.org/sites/default/files/ICH_Q14_Guideline_2023_1116.pdf. Accessed September 2026.
- US Food and Drug Administration. Q2(R2) Validation of analytical procedures: guidance for industry. Docket FDA-2022-D-1503. Silver Spring (MD): FDA; March 2024. Available from: www.fda.gov/regulatory-information/search-fda-guidance-documents/q2r2-validation-analytical-procedures. Accessed September 2026.
- European Medicines Agency. ICH Q2(R2) Validation of analytical procedures – scientific guideline. EMA/CHMP/ICH/82072/2006. Effective 14 June 2024. Amsterdam: EMA; 2023. Available from: www.ema.europa.eu/en/ich-q2r2-validation-analytical-procedures-scientific-guideline. Accessed September 2026.
- Code of Federal Regulations. Title 21, section 211.165: Testing and release for distribution. Washington (DC): Office of the Federal Register; current electronic edition. Available from: www.ecfr.gov/current/title-21/chapter-I/subchapter-C/part-211/subpart-I/section-211.165. Accessed September 2026.
- Code of Federal Regulations. Title 21, section 211.194: Laboratory records. Washington (DC): Office of the Federal Register; current electronic edition. Available from: www.ecfr.gov/current/title-21/chapter-I/subchapter-C/part-211/subpart-J/section-211.194. Accessed September 2026.
- Ministry of Health and Family Welfare (India). Notification G.S.R. 922(E), 28 December 2023, amending Schedule M of the Drugs Rules, 1945. The Gazette of India, Extraordinary, Part II, Section 3(i). Gazette reprint. Available from: pharmadocx.com/wp-content/uploads/2024/01/Notified-Schedule-M-dt-28.12.2023-1.pdf. Accessed September 2026.
- US Food and Drug Administration. Analytical procedures and methods validation for drugs and biologics: guidance for industry. Docket FDA-2015-N-0007. Silver Spring (MD): FDA; July 2015. Available from: www.fda.gov/regulatory-information/search-fda-guidance-documents/analytical-procedures-and-methods-validation-drugs-and-biologics. Accessed September 2026.
- United States Pharmacopeial Convention. General chapter <1225> Validation of compendial procedures. USP 32-NF 27 (historical edition). Rockville (MD): USP; 2009. Available from: www.drugfuture.com/pharmacopoeia/usp32/pub/data/v32270/usp32nf27s0_c1225.html. Accessed September 2026.
- ECA Academy. Proposed revision of USP <1225> published in the Pharmacopeial Forum [news]. Heidelberg: ECA; 25 November 2025. Available from: www.gmp-compliance.org/gmp-news/proposed-revision-of-usp-1225-published-in-the-pharmacopeial-forum. Accessed September 2026.
- United States Pharmacopeial Convention. General chapter <1226> Verification of compendial procedures. USP 32-NF 27 (historical edition). Rockville (MD): USP; 2009. Available from: www.drugfuture.com/pharmacopoeia/usp32/pub/data/v32270/usp32nf27s0_c1226.html. Accessed September 2026.
- International Council for Harmonisation. ICH harmonised tripartite guideline Q3A(R2): Impurities in new drug substances. Current Step 4 version dated 25 October 2006. Geneva: ICH; 2006. Available from: database.ich.org/sites/default/files/Q3A%28R2%29%20Guideline.pdf. Accessed September 2026.
- International Council for Harmonisation. ICH harmonised guideline M7(R2): Assessment and control of DNA reactive (mutagenic) impurities in pharmaceuticals to limit potential carcinogenic risk. Final version adopted 3 April 2023. Geneva: ICH; 2023. Available from: database.ich.org/sites/default/files/ICH_M7%28R2%29_Guideline_Step4_2023_0216_0.pdf. Accessed September 2026.
Technical and educational content for pharmaceutical professionals, not legal or regulatory advice. The SOP above is a template requiring local qualification, validation and Quality Assurance approval before use. Acceptance criteria must be verified against the current pharmacopoeial and ICH editions applicable to your product. Pharmacopoeial texts, ICH guidelines and Indian statutory instruments change between editions. Reviewed September 2026 by Darshan Singh, pharmaceutical QA/QC and regulatory affairs, 23+ years.